Cardiac arrest is not a gentle process. Blood flow to the brain stops. Measurable electrical activity in the cortex flatlines within about 20 seconds. By every standard of clinical neuroscience, there should be nothing after that — no experience, no memory formation, nothing to recall.
And yet a consistent fraction of people resuscitated from cardiac arrest report that something happened. These are near-death experiences.
Not confusion. Not fragments. Structured, detailed, emotionally overwhelming experiences that they describe afterwards as more real than ordinary waking life, and that change how they live.
That is the phenomenon. Explaining it is a different problem, and the field has made more progress in the last five years than in the previous forty.

What Is a Near-Death Experience?
A near-death experience is a reported conscious experience occurring during a period of severe physiological crisis — most often cardiac arrest, but also trauma, anaesthetic complication or drowning.
Psychiatrist Bruce Greyson developed the standard measure, the Greyson NDE Scale, in 1983. It scores sixteen features across four clusters:
| Cluster | Features |
|---|---|
| Cognitive | Time distortion, accelerated thought, life review, sudden understanding |
| Affective | Peace, joy, cosmic unity, encountering a light |
| Paranormal | Vivid senses, apparent extrasensory perception, precognitive vision, out-of-body sensation |
| Transcendental | Entering an unearthly realm, encountering beings or deceased people, reaching a border or point of no return |
A score of 7 or above out of 32 is conventionally treated as an NDE. Roughly 10 to 20% of cardiac arrest survivors report one.
The Features Are Strikingly Consistent
What makes the phenomenon a research subject rather than a curiosity is the convergence.
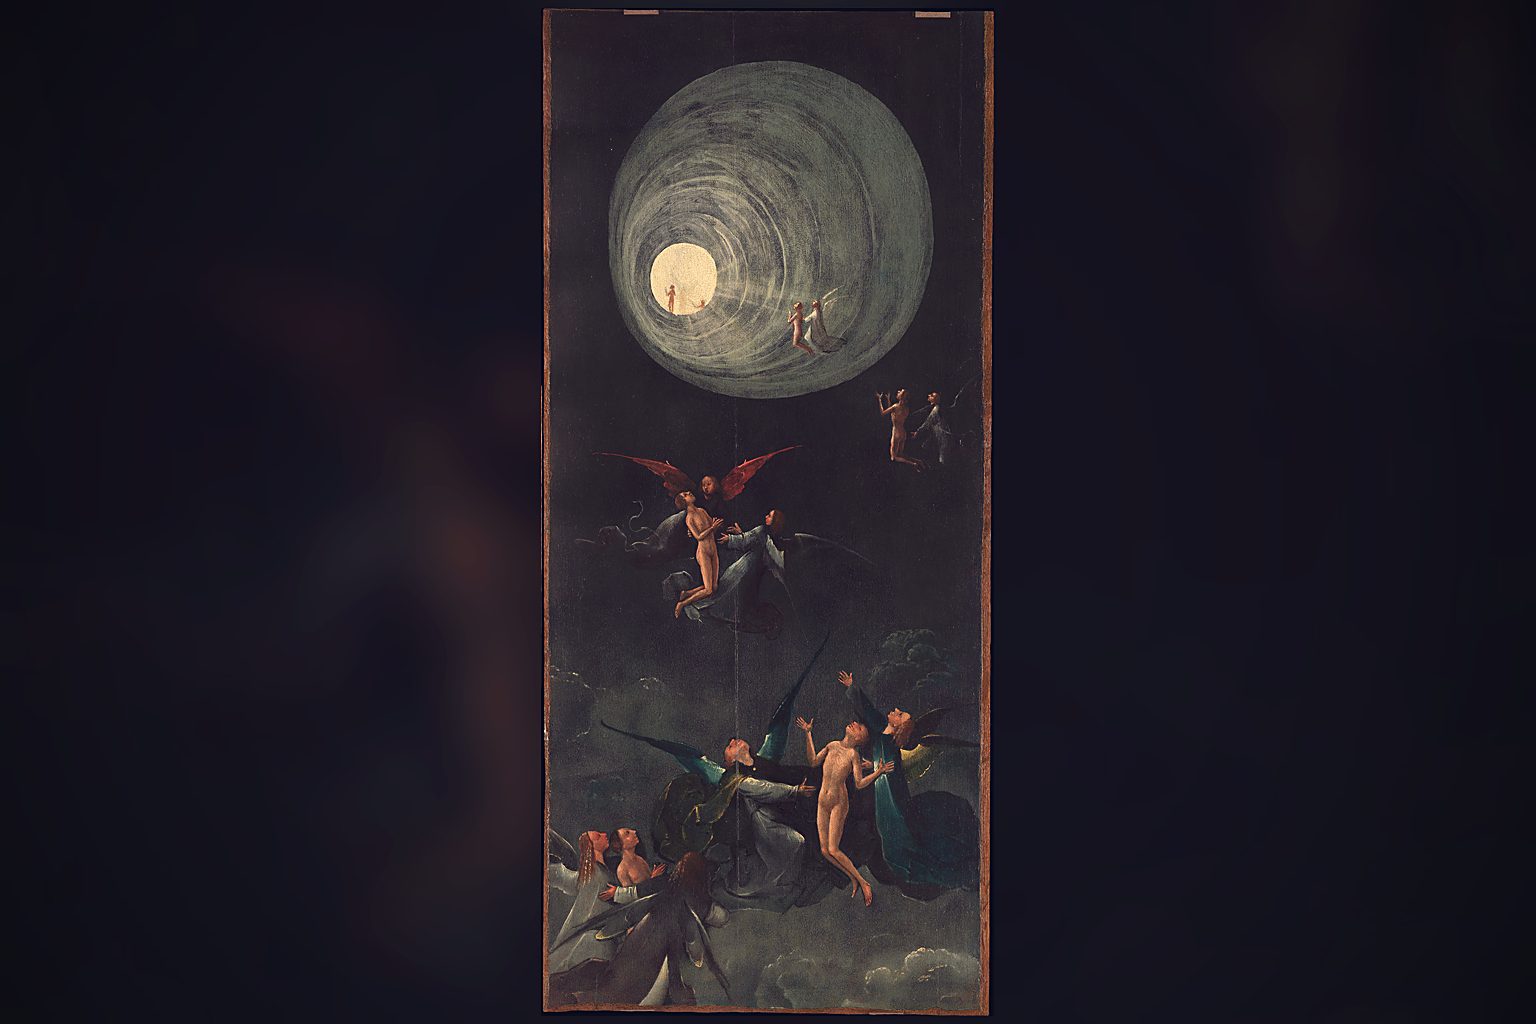
Across cultures, ages, religious backgrounds and degrees of prior knowledge, reports cluster around the same elements: detachment from the body, movement through a dark space or tunnel, a light, a review of one’s life from an unusual perspective — often including how one’s actions felt to other people — a boundary, and a return.
Cultural details vary. The identity of the beings encountered follows the person’s background. The structure does not.
And the aftermath is measurable. Longitudinal work by Greyson and others documents durable changes: reduced fear of death, decreased materialism, increased altruism, sometimes difficult social consequences. People who have had one do not treat it as a dream. That distinction — reported almost universally — is itself a datum.
What the Recent Research Found
This is where the field has genuinely moved.
AWARE (2014). Led by Sam Parnia, this was the first large prospective study designed to test out-of-body claims. It examined 2,060 cardiac arrests across multiple hospitals, with shelves bearing hidden images installed in resuscitation areas so that anyone reporting a ceiling-level viewpoint could be tested.
The result was largely negative on the hidden targets — almost no arrests happened in rooms with the shelves. But one case was notable: a patient described events during his resuscitation, including auditory details, that were subsequently verified and that corresponded to a period when he should have had no cortical function.
One case is not proof. It is a reason to keep looking.
AWARE II (2023). Parnia’s follow-up, published in Resuscitation, monitored patients during CPR with EEG and cerebral oximetry. It found something unexpected: spikes of near-normal EEG activity — gamma, delta, theta, alpha and beta — emerging up to 60 minutes into CPR, in patients with no pulse.
The dying brain surges. In 2013, Jimo Borjigin‘s group at Michigan reported that rats undergoing cardiac arrest showed a transient surge of highly synchronised gamma oscillations — the frequency band associated with conscious integration — in the seconds after the heart stopped. Activity was higher than in the waking state.
In 2022, a team led by Raul Vicente published an accidental human recording: an 87-year-old patient was undergoing EEG for seizures when he suffered a fatal cardiac arrest. The recording captured the transition, and it showed a similar gamma surge in the thirty seconds around death, with patterns resembling those seen in memory retrieval and dreaming.
That is a mechanism worth taking seriously. The brain may not fade out. It may spike — briefly, intensely, in exactly the activity band associated with vivid recall.
The Competing Explanations
Cerebral hypoxia. Oxygen deprivation produces tunnel vision, euphoria and hallucination — pilots in high-G centrifuge training report tunnel vision and brief dreamlike states. But hypoxia typically produces confusion and poor memory, whereas NDEs are reported as exceptionally clear and are recalled with unusual stability over decades.
The gamma surge. The strongest current candidate. A final burst of synchronised activity could produce an intense, memory-rich experience compressed into seconds and later recalled as extended. It fits the clarity, the life review, and the sense of hyper-reality.
REM intrusion. Some people are prone to REM states bleeding into waking consciousness. Kevin Nelson’s work found NDE reporters have a higher rate of this. It may explain the dreamlike content and paralysis elements.
Endogenous neurochemicals. Endorphins, ketamine-like NMDA blockade, and DMT have all been proposed. The DMT link is suggestive — experiences score similarly on NDE scales — but endogenous concentrations appear far too low to be responsible.
Temporal lobe activity. Stimulation of the temporoparietal junction can induce out-of-body sensations reliably, as Olaf Blanke demonstrated. This is a real, reproducible mechanism for one specific feature.
It is what it reports. The survivalist reading: consciousness continues, and the reports describe it. This is not currently testable, and its advocates generally acknowledge that the verification evidence is thin.
The Case That Keeps the Question Open
The hard problem for every physiological explanation is veridical perception — cases where a patient reports specific, checkable information they should not have had access to.
The most-cited is Pam Reynolds, who in 1991 underwent a “standstill” procedure to remove a basilar aneurysm: body cooled to 15°C, heart stopped, blood drained from the head, EEG flat, clicking devices in both ears to confirm absence of brainstem response. She later described the surgical saw, specific conversation in the theatre, and details of the procedure that appeared to match.
The case is genuinely striking. The counter-arguments are also serious: the periods she described may correspond to times when she was under anaesthesia but not in standstill; anaesthesia awareness is a documented phenomenon; auditory information can reach a patient through bone conduction; and the account was recorded some time afterwards, allowing for reconstruction.
This is the honest state of the evidence: a small number of compelling anecdotes, none yet captured under controlled conditions, which is exactly why AWARE installed the hidden shelves and exactly why the near-total absence of hits matters.
Why It Matters Either Way
There is a version of this topic that treats the whole question as a referendum on the afterlife. That framing wastes what is actually interesting.
Whatever NDEs are, they establish something significant about consciousness: experience can occur, and be encoded into durable memory, during states in which our models say neither should be possible. The AWARE II finding of organised EEG activity an hour into CPR is a genuine surprise about what a dying brain does.
That is a question about the mechanism of consciousness — the same territory Descartes was groping at when he picked the wrong organ for the right question. How distributed neural activity becomes unified experience remains unsolved, and the boundary conditions are where unsolved problems usually give something up.
And the phenomenology deserves its own note. The life review — in which people report experiencing their own actions from the perspective of those affected by them — is a remarkably specific feature to recur across cultures with no shared expectation. It is the same structure that appears in traditions of judgement across religious literature, independently arrived at.
Frequently Asked Questions
What is a near-death experience?
A reported conscious experience during severe physiological crisis, usually cardiac arrest. It is measured with the Greyson NDE Scale, which scores sixteen features including peace, out-of-body sensation, a tunnel, a light, a life review and encounters with beings.
How common are near-death experiences?
Roughly 10 to 20% of cardiac arrest survivors report one, depending on the study and the criteria used.
What did the AWARE study find?
The 2014 AWARE study examined 2,060 cardiac arrests and installed hidden images to test out-of-body claims. Almost no arrests occurred in rooms with the targets, so the test was largely inconclusive, though one patient described verified auditory details from a period without expected cortical function.
What did AWARE II find?
Published in 2023, it monitored patients during CPR with EEG and found spikes of near-normal brain activity — gamma, delta, theta, alpha and beta — emerging up to 60 minutes into resuscitation in patients with no pulse.
Does the brain surge at death?
Evidence suggests it may. A 2013 rat study by Jimo Borjigin’s group found a surge of synchronised gamma activity after cardiac arrest, higher than in the waking state. A 2022 human EEG recording captured a similar gamma surge around the moment of death.
Is DMT responsible for near-death experiences?
Unproven. DMT experiences score similarly to NDEs on standard scales and DMT rises after cardiac arrest in rats, but measured endogenous concentrations appear far too low, and NDEs occur in situations without cardiac arrest.
What is the Pam Reynolds case?
A 1991 surgery in which a patient under a standstill procedure — cooled, heart stopped, flat EEG — later described the surgical saw and theatre conversation. It is the most-cited veridical case, though critics note the described events may correspond to periods outside standstill.
Do near-death experiences change people?
Longitudinal research documents durable changes, including reduced fear of death, decreased materialism and increased altruism. Experiencers consistently describe the event as more real than ordinary waking life.
Conclusion: The Spike, Not the Fade
For a long time the assumption was that the brain fades out — activity declining smoothly toward zero, with nothing left to generate an experience.
The recordings say otherwise. What the evidence now suggests is that at the moment the heart stops, something in the brain surges — a brief, intense, highly synchronised burst in the exact frequency band associated with vivid conscious recall, and then organised electrical activity flickering back, in some patients, up to an hour into CPR.
That does not settle what NDEs are. A gamma surge could be the mechanism that produces the experience, or the mechanism that allows an experience to be remembered.
But it does change the shape of the question. The last thing a dying brain does, apparently, is not go quiet.
Continue Reading
- DMT: The Molecule Your Neurons Make for No Known Reason — The brain does synthesise DMT. The measured amounts are orders of magnitude too low to do anything. Both facts are…
- Lucid Dreaming: The Message Sent From Inside a Dream — In 1975 a sleeping man moved his eyes in a pre-agreed pattern and proved lucid dreaming is real. What the brain does…
- Demonic Possession vs Mental Illness: The Argument That Never Ended — For thousands of years, madness meant possession. Then psychiatry relabelled the symptoms and offered drugs that work…